
Luteal phase: What Happens After an Egg Is Released
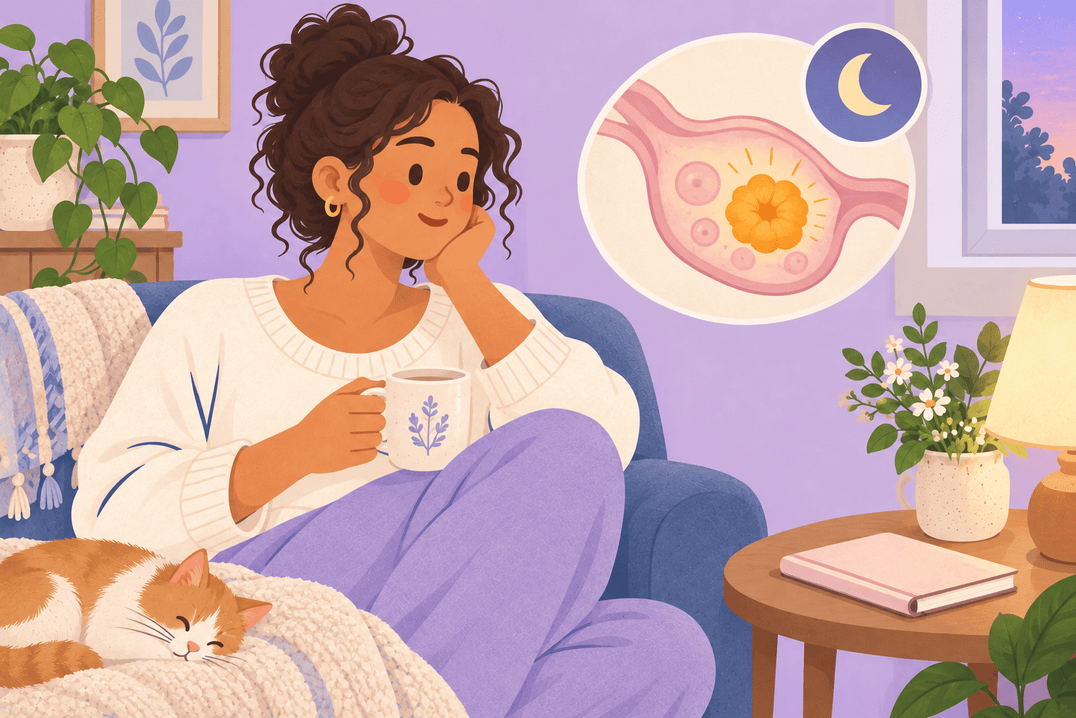
The luteal phase is the part of an ovulatory cycle after an egg is released and before the next period. The structure left behind in the ovary produces progesterone, helping prepare the uterine lining for a possible pregnancy.
Understand the change after ovulation
If pregnancy does not develop, hormone levels fall and bleeding begins. The timing is not identical for everyone. A calendar that automatically subtracts 14 days from a predicted period is estimating a date, not measuring your hormone production.
The follicular phase guide explains the earlier part of the cycle and why assumptions about ovulation can also change an estimated luteal length.
Avoid diagnosing progesterone levels from symptoms
Breast tenderness, bloating, or mood changes do not tell you how much progesterone is circulating. They also cannot reliably distinguish a cycle that will end in a period from early pregnancy.
If a period is late and pregnancy is possible, follow pregnancy test timing guidance. An app’s estimated ovulation date should not be treated as a confirmed biological event.
Interpret test results with their purpose in mind
A suitably timed progesterone measurement can support evidence of recent ovulation. However, progesterone changes substantially over short periods. A single result does not reliably assess the quality of the entire luteal phase.
There is also uncertainty around the diagnosis called luteal phase deficiency. Specialist guidance does not support treating an isolated short estimate as proof that it caused infertility or a pregnancy loss. That distinction matters when advertisements promise to correct a supposed deficiency from symptoms alone.
Bring a question rather than a conclusion
If you repeatedly notice a short interval between an ovulation signal and bleeding, record which method you used and discuss the pattern. Ask whether the dates are reliable, whether another condition needs investigating, and what a proposed treatment is expected to achieve.
Do not begin progesterone or other hormonal treatment based solely on an app calculation. Treatment during fertility care follows a specific clinical plan and should not be copied from another person’s protocol.
Count estimated days with the starting point visible
For a tracking record, keep the estimated ovulation date and the first day of the next full period alongside each other. If you count an interval, state which marker you used: an app estimate, a positive LH test, or a temperature change. Those markers do not all identify the same moment, so the resulting number is an estimate too.
Use the same counting convention across your record and show the underlying dates to the clinician. Mark preceding spotting separately instead of silently changing the endpoint. A short calculated interval in one cycle is not enough to diagnose a progesterone problem or explain a pregnancy loss.
The comparison of fertility tracking methods explains why timing markers can disagree. If short intervals recur, ask whether the dates are sufficiently reliable and whether an underlying condition needs attention. Do not assume that making the calculated interval longer with a medicine would improve the chance of pregnancy.
References
- Office on Women’s Health: Your menstrual cycle (opens in a new tab)
- ASRM: Diagnosis and treatment of luteal phase deficiency (opens in a new tab)
- ASRM: Fertility evaluation (opens in a new tab)
- NHS: Doing a pregnancy test (opens in a new tab)
- NICE: Investigation of fertility problems (opens in a new tab)
- ASRM: Am I ovulating? (opens in a new tab)

Lifeing Editorial
Stories for a little more understanding, a little more reassurance, and the everyday moments in between.
Related posts

Male infertility evaluation: What to Expect at an Appointment